
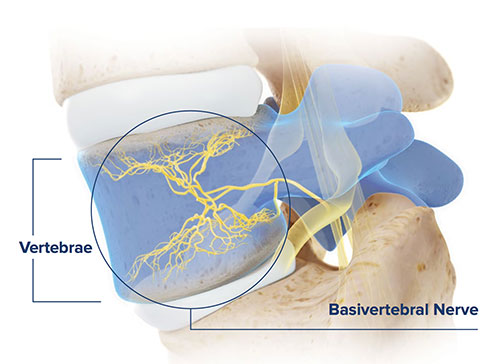
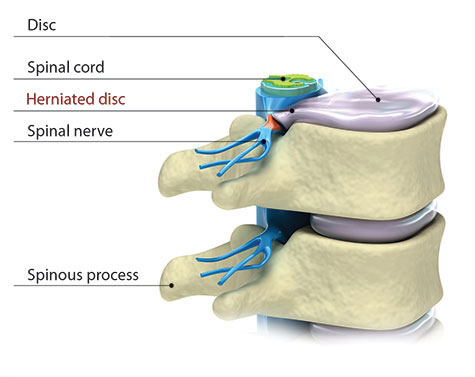
Learn about the shock-absorbing discs that separate the bones in the spine.

 About Spinal Deformities
Spinal deformities are typically a painless condition that causes an abnormal curvature in the spine. This will often create a rotation of the spine and rib cage, which creates asymmetry of the shoulders, trunk, and waist. Although most cases of spinal deformities are mild, severe deformities can often be disabling. Certain conditions can help cause spinal deformities such as cerebral palsy, but in most cases the causes are unknown.
 The three main types of scoliosis are Functional, Neuromuscular, and Degenerative. Functional scoliosis is where the spine is normal, but eventually an abnormal curve starts to develop due to another aliment in the patient’s body such as having one leg longer than the other. Neuromuscular scoliosis can usually be much more severe since the condition is present at birth. This type of scoliosis is due to the failure of the spine bones to properly form, or fail to correctly separate from each other. People born with birth defects or cerebral palsy can often have neuromuscular scoliosis. Degenerative scoliosis is found in adults where the weakening of normal ligaments and other soft tissues of the spine can lead to an abnormal curve in the spine. Many times this can be linked to the patient having complained about arthritis. Idiopathic scoliosis is not linked to a known cause, but it is the most common type of scoliosis in adolescents. Doctors are unsure what causes this type of scoliosis, but it is suggested that it is hereditary because the disorder tends to run in families.
 Most of the time the patient is unaware of the curvature in their spine and is noticed by someone other than himself or herself. The most common symptom of scoliosis is a curve in the spine. Some of the warning signs to look for are shoulders at different heights, appearance of a uneven waist, rib cages at different heights, leaning of entire body, fatigue, backache, low-back pain and head not aligned with the pelvis. These signs and symptoms typically begin during the child’s growth spurt. Boys and girls develop mild scoliosis around the same rate, but girls have an increased risk of the scoliosis worsening. Severe scoliosis (a curve greater than 100 degrees) can create dangerous problems by making it more difficult to breathe and the heart to pump properly.
 If there is uncertainty that you or your child might have scoliosis, it is best advised to see a scoliosis specialist to get evaluated. It is not uncommon for pediatricians and schools to conduct routine examinations (Adam’s Forward Bend Test) for scoliosis. This test has the person take off their shirt and touch their toes, which exposes the spine to the examiner so he or she can easily detect any abnormal spinal curvatures. Most of these screenings take place in the fifth or sixth grade. Further testing can be done by taking an X-ray from the front and the side to get a clearer view of the curvature of the spine. Height and weight is routinely measured because the more remaining growth the patient has, the greater potential of the scoliosis to eventually worsen. It is advised to have a follow up examination to compare the results of your previous visits to get a better idea of the pace of the spinal curving.
 Treatment of scoliosis is individualized and is directly based on the severity of the curve and the potential of the spine developing even worse. The three main categories of most scoliosis treatment include observation, bracing, and surgery. Observation is usually the most common route. If the doctor recommends wearing a brace, this treatment is designed to further prevent worsening of the curvature in the spine rather than to reverse the scoliosis back to a completely straight spine. Surgery consists of connecting two or more vertebrae in the spine together with new bone using metal rods, screws or wires to maintain a straight posture while the spine heals. Neuromuscular scoliosis is usually the most demanding on aggressive treatment and many of these patients might need surgery.
Experimental testing is being researched to see if a patient’s blood can give doctors insight about if the scoliosis is likely to worsen in the future. The implementation of school examinations for scoliosis helps parents be aware of their child’s situation before a more severe problem eventually develops. Early detection can drastically help the person from maybe needing only observation treatment and avoiding a risky surgery. The vast majority of people diagnosed with some degree of scoliosis will often live normal, active and healthy lives.
With pediatric scoliosis, childhood bones are still in formation until maturity at about age 18. This makes it very important to discover scoliosis early before the spinal curve worsens and becomes more difficult to straighten. Consequently, most elementary schools have school nurses who are trained to check young children at around age 10 for an abnormal curve. The nurses use a simple Adam’s Forward Bending Test to quickly spot an abnormal spinal curve. This can also be done by the parent at home to spot scoliosis or an abnormal curve early.
A hump can indicate there is a potential spinal rotation or curvature. However, this is NOT a not a formal diagnosis. A scoliosis specialists will order an X-ray to measure the precise angle, called a “Cobb angle,” to confirm or rule out scoliosis. The Cobb angle is measure in degrees to categorize how severe the spine is curved sideways. Using an X-ray image of the spine, the scoliosis specialist identifies the most tilted spine vertebra at the top of the spinal curve, and then the most tilted vertebrae at the bottom of the curve, and then draws straight lines along the top and bottom edges of these two bones to measure the angle where those lines cross.
An important consideration for the parent is the X-ray procedure itself. While an X-ray is painless it uses radiation to generate the image of the upper torso. Exposing a child to a heavy dose of radiation several times during assessent and treatment is not ideal because of the lifelong implications of exposure to radiation. Consequently, the most advanced spine centers now use an EOS diagnostic device that uses a very low dose of radiation to obtain the image of the spine.
Texas Spine and Scoliosis was one of the first spine centers in the nation to purchase and install an EOS X-ray machine. For example, there are only about 100 EOS machines installed across the United States, and only about 500 worldwide.
The EOS machine also scans the patient standing up and bending to show the spine and discs under load. Because the machine is expensive few practices can afford the investment in such a high-end diagnostic machine.
With that said a parent would be well-advised to seek out a spine center that has an EOS X-ray machine because a child will need several of these scans as they proceed through treatment.
About 80% of scoliosis cases are diagnosed during adolescent growth spurt between the ages of 10 and 15. About 15% of cases are labeled Juvenile Scoliosis and discovered at ages 3 to 10. Infantile Scoliosis relates to curves or deformity from birth to 3 years and is rare with only 1% of cases.
Interestingly, while boys and girls are at equal risk of being diagnosed with scoliosis, girls are at 10 times higher risk of having a curve that worsens and requires surgery. For example, a girl is 9 times at more risk to have a curve measuring over 40 degrees compared to a boy. It’s theorized that the higher risk is from a girl having an earlier growth spurt and the effect of hormones.
There is some evidence that scoliosis may be inherited from a biological parent or grandparent. But there are cases of twins where only one develops scoliosis. So there are still many unknowns about what causes scoliosis.
Adult scoliosis can appear with age and degeneration of the spine, often appearing along with pain symptoms in the neck, back, shoulders, hips or legs. The abnormal curve over time causes muscle fatigue and can pressure and damage internal organs which can reduce life expectancy.
Another adult deformity problem is called Flatback Syndrome which is caused by Harrington Rods. These rods were the common surgical correction option for scoliosis beginning in 1960 and were commonly used for scoliosis correction up to about 1990. Harrington Rods were straight rods installed along the spine with hooks attached to vertebrae to reduce a spinal curve. The problem is that in the effort to straighten the abnormal side curve, the system removed the natural healthy curve of the spine. This caused the back to become “flat” causing many serious problems as the person got older, including muscle fatigue and pain symptoms. It’s estimated that 1 million people over the 30-year period had Harrington Rods installed.
The common treatment for Flatback Syndrome is to replace the Harrington Rods with newer instrumentation that restores the normal curve to relieve muscle fatigue and pain symptoms.
Other cases of Flatback Syndrome could also relate to spinal fusion surgery that wasn’t successful, again removing the natural health curve in the spine. Revision surgery is sometimes needed to correct these Flatback cases.
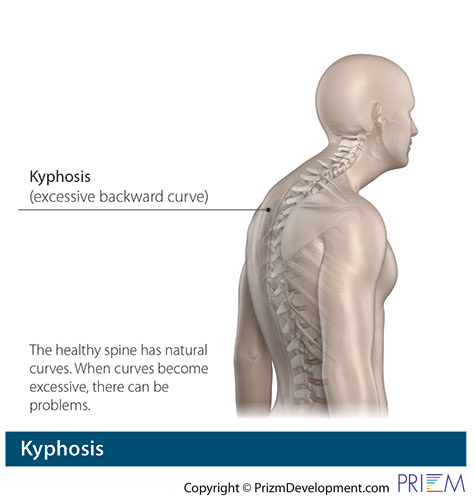
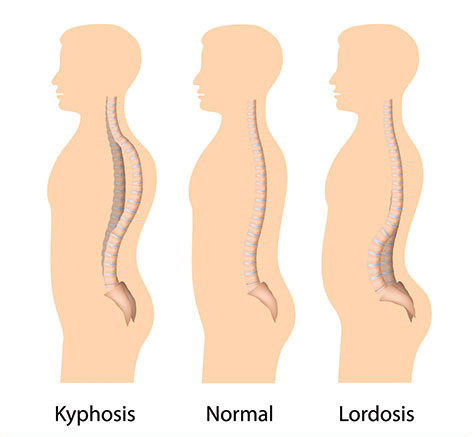
Another spinal curve, called kyphosis, is often linked to aging is where the person develops a hunched over appearance. As a person ages the front part of a vertebra can become wedge-shaped to weaken the spine.
Scheuermann's Kyphosis can appear with puberty and the growth spurt, where the vertebrae morph into a wedge shape, making the upper back curve rigid.
Postural kyphosis can appear in teen years related to poor posture.
 When caught early in childhood or teen years, the scoliosis specialist has more non-surgical treatment options for children and teens, such as wearing a brace to arrest the progression of the curve. Bracing, conversely, is typically not a treatment option for adults.
Another form of bracing that involves a minimally invasive surgery is called Vertebral Tethering. The surgeon accesses the side of the adolescent spine and attaches a heavy cord that is anchored to several vertebrae and then adjusted and tightened to prevent worsening of the spinal curve.
The other positive aspect of treatment for children and teens is that if scoliosis surgery is necessary to straighten the spine, younger spines are far more flexible for correction than those who are over the age of 40. Consequently, the proficient scoliosis surgeon is often able to return teen girls to active sports like gymnastics and cheerleading. Even boys are sometimes allowed to return to contact sports like football once they achieve a full recovery from the surgery and approved by the scoliosis surgeon.
Scoliosis surgery uses special instrumentation with rods that attach to vertebrae and de-rotate the spine like straightening a bent corkscrew. The instruments stay in position to hold the spinal correction and are not removed after surgery.
For an adult with scoliosis, or degenerative deformity, delaying surgery can create problems. Aside from the pain symptoms, a spinal curve can pressure internal organs causing permanent damage that shortens a lifespan. Secondly, the older a person gets, the less flexible the spine is to correction. The surgeon must be extremely careful during this type of surgery to not affect the spinal cord which could cause paralysis.
Decades ago in the 1990s a general orthopedic surgeon might do scoliosis surgery. Today, however, orthopedic specialists are typically sub-specialized and “fellowship-trained” to focus on just a single area of the body. So today, you have hip surgeons, knee surgeons, shoulder surgeons, hand surgeons, foot surgeons, etc.
General orthopedic surgeons are often found in smaller cities where they are expected to provide a variety of care like fractures and routine orthopedic surgeries. Joint replacement specialists, including knee, hip and shoulder replacement, can be found in smaller cities as well as the technology and expertise has been around for decades.
Scoliosis, however, is a more narrow niche and the most experienced scoliosis surgeons are typically located in large cities. For a parent looking for a scoliosis surgeon for a child or teen, they should recognize they most likely will have to travel to a regional spine and scoliosis center to access the highest level of proficiency where the surgeon is doing a high number of scoliosis surgeries a year.
Scoliosis is one such area that requires a physician who typically specializes in spinal deformity. Just like anything else, practice makes perfect, and that is especially the case when working around the spinal cord. So one question to ask in searching for a scoliosis surgeon is how many scoliosis surgeries they perform each year.
Today, board-certification is a standard requirement. For a surgeon, fellowship training is the most desirable. A fellowship is an extra year of training in a specific specialty niche working in a center with some of the best surgeons in the nation in that category.
So for scoliosis, the person should look for fellowship training in scoliosis and spinal deformity, either in orthopedic surgery or neurosurgery. Most scoliosis surgeons also belong to Scoliosis Research Society so they access advanced research on scoliosis. The Scoliosis Research Society has a FIND A PHYSICIAN page on their web site at: srs.org/Patients.
Dr. Matthew Geck, a nationally known expert on adult and adolescent scoliosis, presents a summary of Clinical Outcomes on Scoliosis.
Dr. Matthew Geck is involved in research that advances the treatment of scoliosis through his association with Dell Medical School in Austin, Texas. This video features Dr. Geck, Assistant Professor of Surgery at Dell Medical School, providing a lecture on minimally invasive scoliosis surgery at the Dell Medical School Grand Rounds in June 2023. The video outlines 2023 clinical outcomes for minimally invasive scoliosis surgery compared to traditional surgery with a single long incision. The video shows dramatic before/after images of successful scoliosis correction.
Dr. Geck is a leader in the development of mini scoliosis surgery that uses three smaller incisions to correct the spinal curve rather than one long incision. The mini scoliosis surgery technique lessens blood loss and disruption to muscles and ligaments in the back. The smaller incisions enable the scoliosis surgery patient to recover more quickly with a less painful rehab.
Few scoliosis surgeons in the United States are trained in mini scoliosis surgery. More information can be found at ScoliosisTexas.com and TexasSpineandScoliosis.com. Dr. Geck maintains an active Austin, Texas scoliosis practice specializing 100% in adult and adolescent scoliosis, which attracts scoliosis patients from across the United States to the nationally known spine center. The spine center is the only spine center in Texas featured on SpineCenterNetwork.com as a regional spine center of excellence.
 |
|
Click here to download |
Click here to download |
 Website Design & All Educational Content © Copyright 2023 Prizm Development, Inc. Developing Centers of Excellence for Better Healthcare.



 We Value Your Privacy